


Chronic Cystitis – Therapy
Protocols · Chronic cystitis · Treatment
Chronic cystitis treatment: the Georgiadis Chronic Cystitis Protocol (GCCP), and why another course of antibiotics is not it
Chronic cystitis is not cured by the treatment that failed to cure it the first ten times. The microbes are in the bladder wall, in biofilms and inside cells, and in the vagina next door; oral antibiotics in the urine barely touch them. The Georgiadis Chronic Cystitis Protocol delivers the right drugs directly into the bladder in a staged schedule, treats the vagina and, when needed, the uterus at the same time, and deals with the strictures and resistant lesions that keep the infection alive. In our experience it brings a definitive end to cystitis in the large majority of women, including those who have had it for a decade or more.
Treatment at a glance
How we decide the treatment
The first step is to put together the right medication, almost always a combination of substances, chosen on four things:
The microbes found, and the ones not yet found
The organisms identified in the urine, vaginal and, where taken, endometrial cultures, and their resistances, decide the antibiotics. But not every microbe shows itself in the first cultures, so the plan also covers the organisms that chronic cystitis typically hides and that early cultures miss.
The lesions
How severe the inflammation is in the urethra, the bladder, the vagina, the cervix and the uterus, as seen on ultrasound, cystoscopy and examination.
The complications
Whether the years of inflammation have left a urethral stricture, a voiding problem, a diverticulum, incontinence: things that keep the infection going and need their own treatment.
The history
How long the cystitis has been there and how many antibiotics it has already survived. The longer and the more, the more resistant the microbe and the longer the course.
Oral and, where the uterus is involved, intravenous antimicrobial treatment runs for one to three months, in some cases longer. Alongside it we use medicines that reduce the most intrusive symptoms, the frequency and urgency, while the infection is being cleared. But oral medication alone does not cure chronic cystitis. That is what the protocol is for.
The Georgiadis Chronic Cystitis Protocol: intravesical instillations
Long-standing lesions of the bladder wall are highly resistant to any treatment that relies on oral antibiotics alone, because the drug concentration that reaches them through the urine is low and brief. Intravesical instillation solves this: a mixture of specific antimicrobial substances, at concentrations that cannot be achieved any other way, is placed directly in the bladder and held against the inflamed wall. This is the core of the protocol and, in most cases of chronic cystitis, a necessity.
How it is done
The procedure is simple and painless. A very thin disposable catheter is passed into the bladder and the pharmaceutical mixture is instilled through it. The patient keeps the solution in the bladder for about two hours, going about her day, and then passes it naturally. There is no systemic absorption to speak of, so none of the side effects of weeks of oral antibiotics.
The two stages
- Induction. Instillations typically three times a week, more or fewer depending on the lesions, for one to two months. This is where the bulk of the inflammation is cleared and the symptoms change.
- Consolidation. A few instillations a month for three to six months, to clear what remains in the deeper layers and to prevent the dormant colonies from re-establishing themselves.
The frequency is adjusted to the findings at cystoscopy and to the response. In our experience the results are decisively positive in the large majority of patients, including the most difficult, long-standing cases with symptoms that had dominated daily life for years.
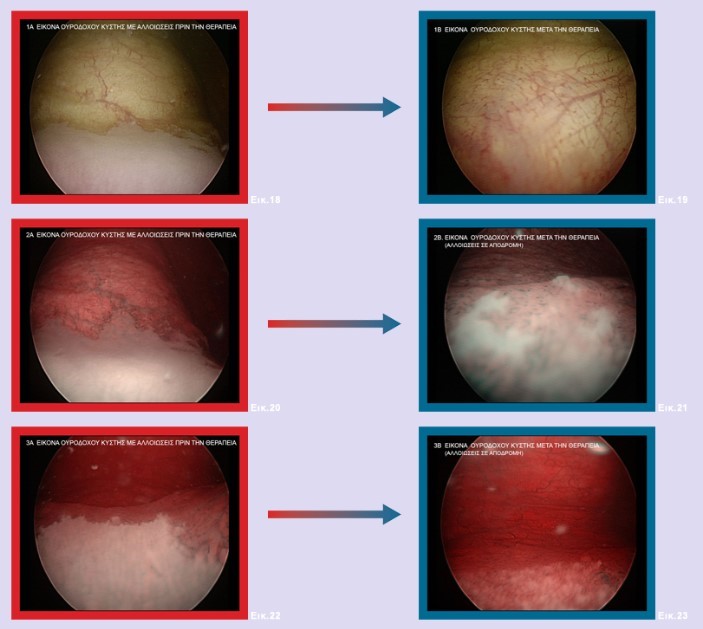
Treating the vagina and the uterus at the same time
Intravaginal treatment
A microbial infection of the vagina coexists with chronic cystitis in the large majority of our patients and must be treated at the same time, or it re-infects the bladder within weeks. When it does not clear with the oral medication, we apply intravaginal preparations: mixtures of the appropriate antibiotic creams, giving high local drug concentrations in the vagina and the lower uterus, where the microbes have usually also settled. Restoring the protective flora afterwards, and vaginal oestrogen in women after menopause, keeps the door closed.
Endometrial infection
When the cultures show that the microbes have reached the endometrium, the treatment is extended: in addition to the oral and local therapy, intravenous antibiotics are needed to eradicate them from the uterus. This matters most for women who want to conceive: in our experience a persistently infected endometrium is a cause of early pregnancy loss and of repeated unexplained IVF failures, and treating it changes the outcome.
Urethral dilation and transurethral cautery
Urethral dilation
Years of inflammation of the urethra and bladder leave, in a proportion of women, a narrowed urethra: a functional or organic stricture that obstructs emptying and makes the cystitis almost impossible to cure until it is recognised and treated. Dilation is a minor procedure under local anaesthesia, very well tolerated, and it removes one of the main reasons for relapse.
Transurethral electrocautery or laser
A small minority of cases, in our experience around one in ten, are so chronic and their lesions so resistant that they do not clear even with the instillations. For these we cauterise the lesions through the cystoscope, with an electrocautery device or alternatively a neodymium (Nd):YAG laser, alongside the antimicrobial treatment. After an initial course of instillations the healing is very good, and nearly all of these women are free of their chronic cystitis within about three months of the procedure.
What the research shows about treating cystitis this way
The principles of the protocol, hidden reservoirs of bacteria, high local drug concentrations, treating the vaginal reservoir, are each supported by the published literature. The combination, and the results we see, are our own.
The bacteria are where oral antibiotics do not reach
E. coli invades the cells of the bladder lining, forms protected communities and goes dormant in reservoirs that later reseed the bladder; this has been shown in the laboratory and in the urine of women and children with cystitis (Rosen 2007, Robino 2014). Children with these intracellular bacteria were about three times more likely to have recurrent infections. Drugs circulating in the blood and urine reach these reservoirs poorly.
Intravesical antibiotics work and are safe
Series of patients with recurrent infections resistant to everything else, treated with antibiotics instilled directly into the bladder (most often gentamicin), report a large proportion becoming infection-free, with negligible absorption into the blood and little emergence of resistance (for example Pietropaolo and colleagues, 2022). Induction followed by maintenance instillations is the schedule most centres converge on.
The vagina is the reservoir
Genetic studies have found identical strains of E. coli in the bowel, the vagina and the bladder of women with recurrent infection. Restoring the vaginal flora, with vaginal oestrogen after menopause and with lactobacilli, reduces recurrences in controlled trials. The principle of treating the vagina alongside the bladder is now mainstream prevention; we take it further and treat the infection there as well.
What the guidelines say, and what we say
Current guidelines for recurrent urinary infection recommend behavioural measures, vaginal oestrogen and short antibiotic prophylaxis, and reserve intravesical antibiotics for refractory cases in specialised hands. Our view is that “refractory” describes most women with chronic cystitis by the time they reach us, and that treating the hidden infection properly from the start spares them years of prophylaxis. The results in this clinic are our own clinical experience; controlled trials of the full protocol have not been done.
What does not cure chronic cystitis
Long-term low-dose antibiotics (“chemoprophylaxis”)
Taking a small daily dose of an antibiotic for months or years to keep the disease quiet. In patients with a history of more than two or three years it brings, in our experience, no practical benefit, and it does harm: it masks symptoms and removes the urgency to treat, it does nothing to stop the inflammation spreading, and it breeds microbes resistant to even the strongest drugs. Many women reach us after six to ten years of prophylaxis and repeated “powerful” antibiotics for Enterococcus, Staphylococcus, E. coli, Proteus, Klebsiella or Chlamydia, with organisms that now resist everything. They can still be treated, but it takes longer.
Vaccines and immunoprophylaxis
Oral bacterial vaccines give a small number of patients moderate improvement: slightly milder symptoms, slightly longer intervals between flares. The published trials agree: a modest reduction in recurrences, nothing more. In our experience the symptoms remain at a level that disturbs daily life, and even long courses leave the preventive effect poor. They are sometimes suggested by gynaecologists and urologists; the results do not justify them as a treatment.
Bladder relaxants and painkillers alone
Anticholinergics, bladder “cocktails” and analgesics make the symptoms more bearable, which has its place during treatment. As the treatment, they leave the infection exactly where it was.
Waiting, and “learning to live with it”
Every year of untreated chronic cystitis means deeper lesions, more resistant microbes, more involvement of the genital tract and a longer eventual treatment. We would urge women to be critical of any plan that consists of yet another antibiotic course, and to seek out urologists with a track record in actually ending cystitis.
What to expect
Before treatment
A full diagnostic work-up: cultures from urine and vagina (and menstrual tissue where indicated), ultrasound of kidneys, bladder and pelvis, uroflowmetry, cystoscopy. Treatment is designed on the findings, not on guesswork. Read how we diagnose chronic cystitis.
During treatment
Visits for the instillations, three a week at first, then a few a month; oral or intravenous antimicrobials; local vaginal treatment; dilation or cautery where needed. Patients from abroad arrange the induction stage in Athens and the consolidation stage with longer intervals. Some women feel worse for a short period as the lesions react; that passes.
After treatment
Cultures to confirm the microbes are gone, a check of the bladder wall, and advice on the vaginal flora, hygiene, hydration and the partner. In our experience the result is a definitive solution without relapse in the large majority of women, including those who had lived with cystitis for years.
Ready to end the cycle?
Send us your history and any results. We will tell you honestly whether the protocol is right for you, how long we expect it to take, and how it can be organised if you live far from Athens.
Frequently asked questions about treating chronic cystitis
Can chronic cystitis be treated without antibiotics?
Not when there is a microbe in the bladder wall, and in our experience there almost always is. What can and should change is the way antibiotics are used: targeted to the organisms actually found, delivered into the bladder and the vagina where the infection lives rather than swallowed for weeks, and finished properly. Cranberry, D-mannose, probiotics and hydration help the bladder; they do not clear a chronic infection.
Can chronic cystitis be cured, or only managed?
In our experience it can be cured in the large majority of women, provided the microbe is identified, the treatment reaches it, and the vagina and any strictures are dealt with at the same time. “Management” with prophylactic antibiotics is what most women have already had, for years, without result.
Is the intravesical treatment painful?
No. The catheter is very thin and disposable, the instillation takes minutes, and the solution is held for about two hours while you go about your day. Most women describe mild discomfort at most.
How long does the treatment take?
Typically one to two months of frequent instillations, then three to six months of occasional ones, with oral medication for one to three months. Very long-standing or resistant cases take longer. Women who have taken years of prophylactic antibiotics need more time because their microbes are more resistant.
Does the protocol work for interstitial cystitis?
For the many women labelled “interstitial cystitis” who in fact have a hidden chronic infection, yes: the label does not change the treatment once the microbe is found. We investigate every interstitial cystitis as a possible chronic bacterial cystitis first. Read interstitial cystitis or chronic cystitis?
Does my partner need treatment?
Often, yes. The microbes pass between partners during sex, and a man’s chronic prostatitis can keep re-infecting a woman’s vagina and bladder. In chronic cases we examine the partner and treat him if needed.
What about the antibiotics I am already taking every day?
Prophylactic antibiotics are stopped as part of the protocol. They do not cure chronic cystitis, they mask it, and they make the microbes harder to kill. The treatment that replaces them is targeted and finite.
Can I be treated if I live abroad?
Yes. Patients come to Athens for the diagnostic work-up and the induction stage, which is the intensive part, and the consolidation stage is arranged with longer intervals. Many of the women on our testimonials page live in other countries.
