


Sexual Dysfunction – Therapy (GERP)
Protocols · Erectile dysfunction treatment
Erectile dysfunction treatment that treats the cause: the Georgiadis Erectile Revivification Protocol (GERP)
Most erectile dysfunction treatment is a pill that forces an erection and leaves the disease alone. Ours is built the other way round. First we find and treat what is damaging the nerves and vessels of erection, which in the men we see is usually chronic inflammation of the prostate. Then, where years of disease have already fibrosed the erectile tissue, we repair it with a combined programme of intracavernosal injections, vacuum therapy, low-intensity shockwaves and PRP (the “P-shot”), applied together, several times a week, for six to sixteen weeks. This page explains both phases, what each method does, what to expect at each stage of erectile dysfunction, and what pills, stem cells and surgery can and cannot do.
The treatment at a glance
Why erectile dysfunction needs two phases of treatment
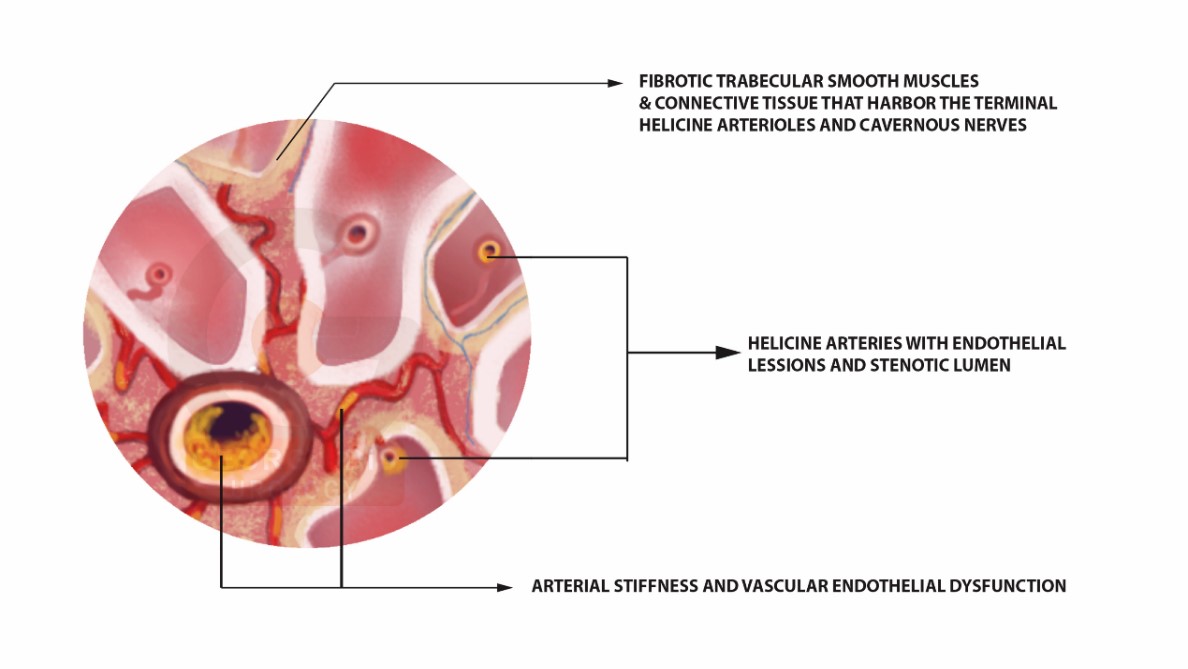
Erectile dysfunction has a cause and an effect. In most of our patients the cause is chronic prostatitis: inflammation that strangles the cavernous nerves as they pass the gland and floods the penis with inflammatory products that damage its arteries. The effect, after enough years, is a change in the penis itself: the smooth muscle of the erectile chambers is replaced by fibrous tissue, the arteries stiffen and the venous trap leaks. The effect is what the man feels. But any treatment that works only on the penis, whether pills, shockwaves or injections, while the cause continues, produces improvement that fades, and the man concludes that “nothing works”. It was not the method that failed; it was the order.
So we treat in two phases, overlapping: the cause first, and the erectile tissue as soon as the cause is under control. In men whose erectile dysfunction is early (stage 1), phase 1 alone is usually enough. From stage 2 onwards, the tissue needs its own treatment. The stages of erectile dysfunction.
Phase 1: treating the cause, usually chronic prostatitis
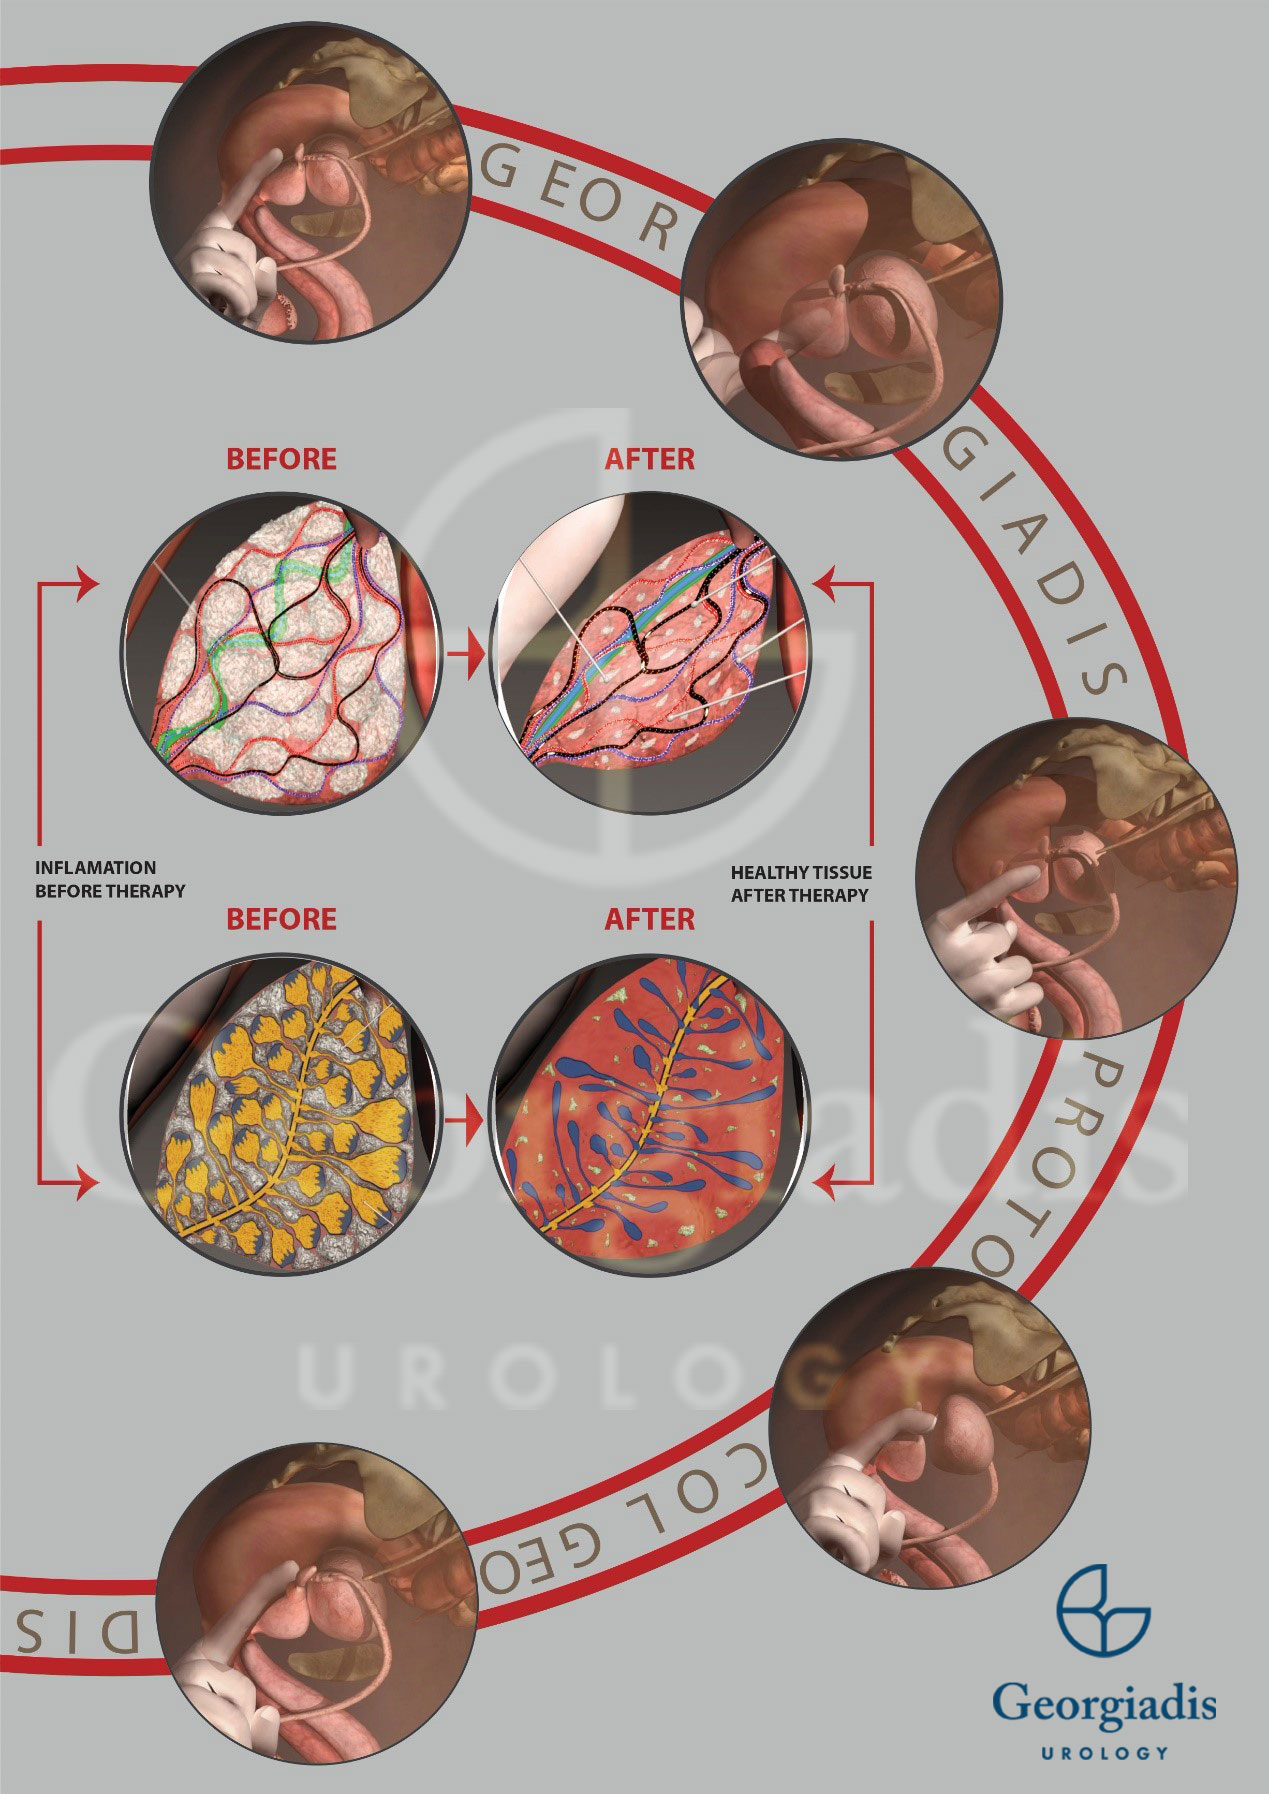
When the cultures, the transrectal ultrasound and the examination show chronic prostatitis, which they do in most of our erectile dysfunction patients, the man is treated with the Georgiadis Protocol for Chronic Prostatitis (GCPP). Its goals are the ones that matter for erection: to clear the prostatic ducts of the pus and organisms that keep the inflammation alive; to soften the fibrotic tissue between the glands; to release the strangled vessels so that blood, oxygen, immune cells and antibiotics reach the tissue; to free the intraprostatic and periprostatic nerve plexus, including the cavernous nerves of erection; and to restore elasticity to the hardened tissue around the urethra. Erections, ejaculation and desire start to improve as the inflammation clears and the nerves are decompressed, usually within the first weeks.
When the cause is something else, vascular disease, diabetes, a medication, a hormonal disorder, it is treated with the relevant specialist in parallel; in practice most of these men have prostatitis as well, and it is treated alongside. How the prostatitis protocol works, stage by stage.
Phase 2: the Georgiadis Erectile Revivification Protocol (GERP)
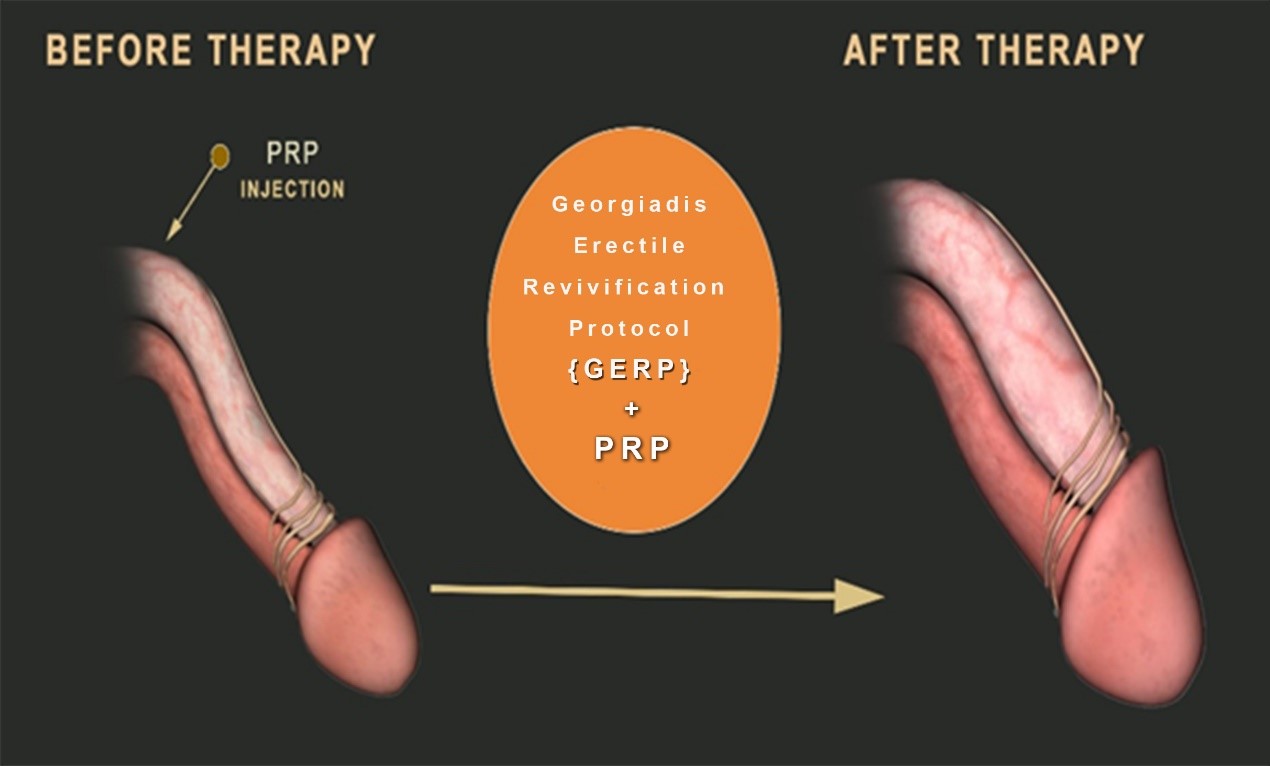
GERP is a rehabilitation of the erectile tissue and its microcirculation: four methods with different mechanisms, applied in the same sessions, three times a week, so that they reinforce each other. It begins a few weeks into the treatment of the prostate.
1. Intracavernosal injections
Small doses of vasoactive agents (prostaglandin E1, alone or combined with papaverine and phentolamine) injected into the erectile chambers with a very fine needle produce a full erection whether or not the nerves are working. Used as a course, not just on demand, they do more than that: repeated full engorgement stretches the fibrosed tissue, opens the cavernous arteries, raises oxygen levels in the chambers, improves the venous trap and stimulates new vessel growth and smooth-muscle recovery. Some men regain spontaneous erections after a course of injections regardless of the original cause. The injection is self-administered after training and is far less unpleasant than men expect.
2. Vacuum erection device
A cylinder over the penis, a pump that draws blood into it, and a ring to hold it. Used therapeutically, without the ring, it is a daily exercise for the erectile tissue: it counters the low oxygen that drives fibrosis, raises growth factors, improves the ratio of smooth muscle to collagen and increases the enzyme that makes nitric oxide. It is also the standard tool for preserving penile length and tissue after prostate surgery.
3. Low-intensity shockwave therapy
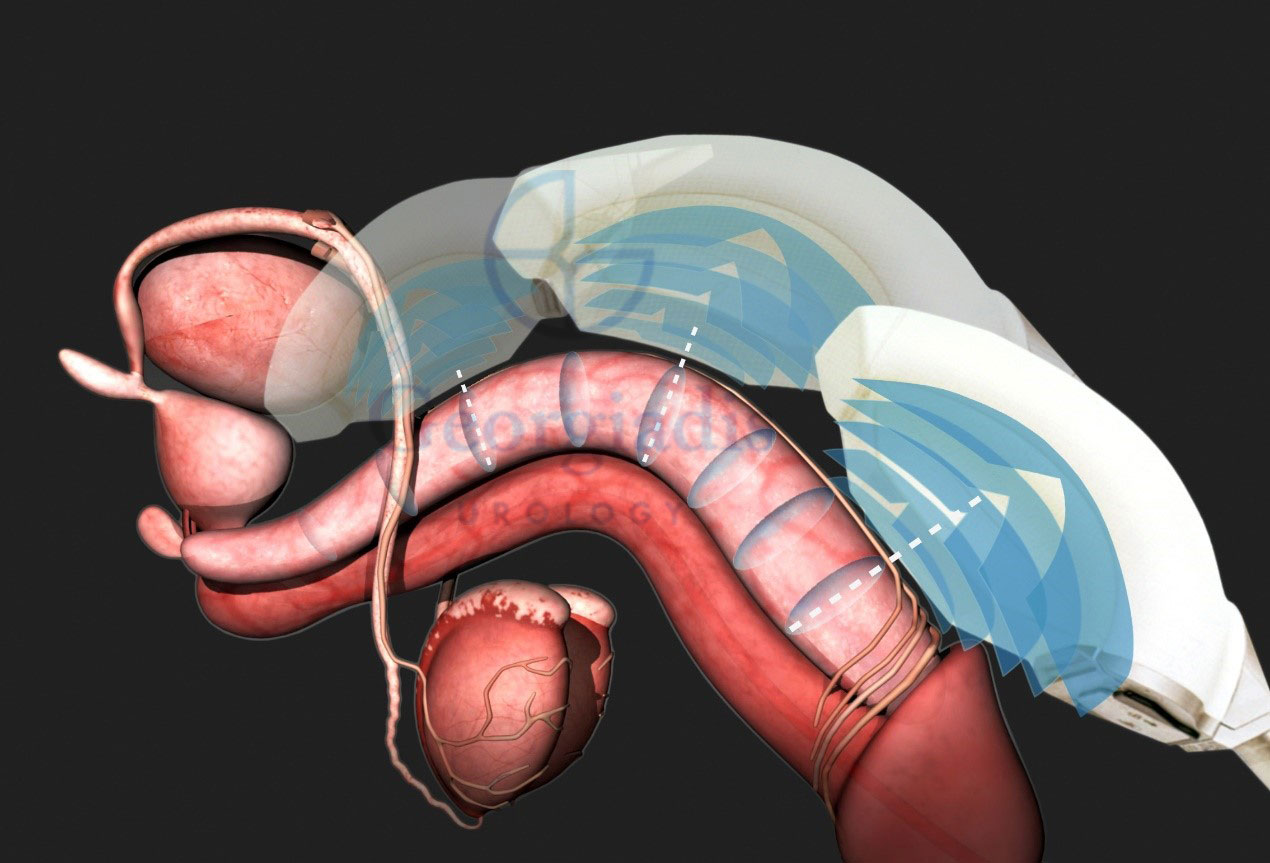
Focused acoustic pulses applied along the shaft and the base of the penis trigger a cascade of repair in the tissue: release of vascular endothelial growth factor and nitric oxide synthase, growth of new small arteries and improved microcirculation, recruitment of the body’s own stem cells, nerve growth factor and nerve regeneration, a fall in inflammation and oxidative stress, regeneration of smooth muscle and elastic fibres, and a reduction in collagen. Shockwaves have a solid evidence base for vascular erectile dysfunction. The criticism that their effect wears off after a year or two is, in our view, explained by the fact that the untreated prostatitis underneath resumes its damage; combined with treatment of the cause, the effect holds.
4. PRP: platelet-rich plasma (the P-shot)
Growth factors concentrated from the man’s own blood, injected into the erectile tissue to promote healing and regeneration. Details, numbers and honest expectations in the next section.
How long, how often
Three sessions a week. For mild cases, with erectile dysfunction of less than a year, six to eight weeks. For men whose problem has lasted more than two years, and in severe cases, up to twelve to sixteen weeks. The injections and vacuum are continued at home between sessions. Penile Doppler at the end measures the change in arterial inflow and venous trapping against the baseline.
PRP for erectile dysfunction (the P-shot): what it is, how many, and honest expectations
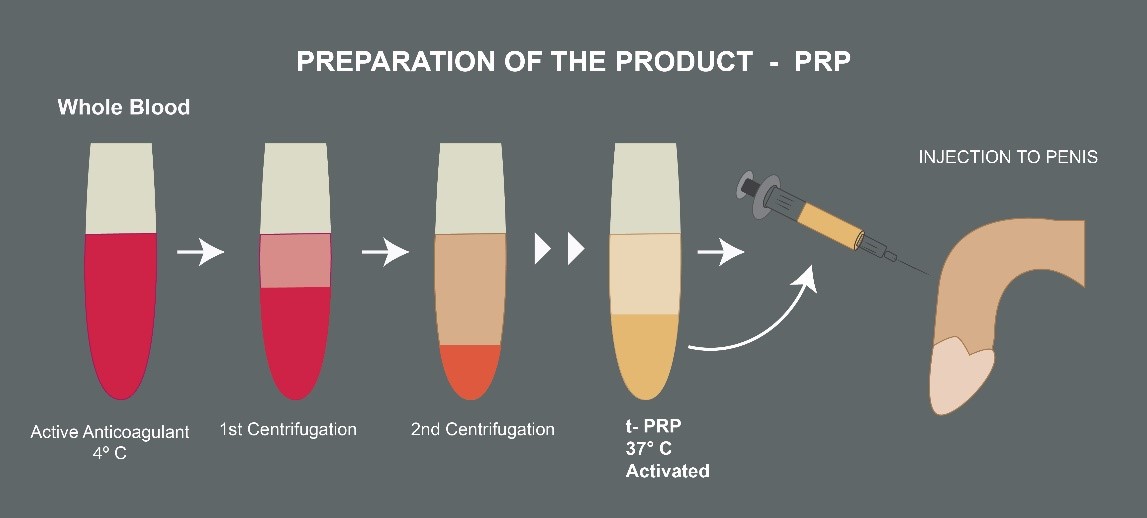
What it is. A sample of the man’s own blood is centrifuged to concentrate the platelets, which carry growth factors (PDGF, VEGF, TGF-beta and others) that signal tissue to repair. The resulting platelet-rich plasma is injected with a fine needle into the erectile chambers, under local anaesthetic cream. The aim is to initiate and multiply the regeneration of smooth muscle, endothelium and nerve endings in tissue that fibrosis has damaged.
How many. In our protocol, three to six injections, four to six weeks apart, directly into the damaged cavernosal tissue. The number depends on how much the tissue has changed on Doppler, on the cause of the fibrosis and whether it is under control, and on aggravating conditions such as diabetes, hypertension and high cholesterol.
What to expect. Men who search for “P-shot before and after” find photographs and promises. Here is what we tell our own patients. PRP is a regenerative stimulus, not an instant result; the change builds over weeks and months. It is not used alone: on its own, in a penis whose nerves are still strangled by an inflamed prostate, it does little, and the clinics that use it alone are the reason its reputation is mixed. Used inside GERP, with the cause treated, it contributes to firmer, more sustained erections, better sensation and, in many men, a visibly fuller penis. It does not enlarge a normal penis, and any clinic that promises size should be avoided. Side effects are minor: bruising and a day or two of tenderness.
Stem cell injections into the penis are experimental: the studies are small, the products unregulated in most countries, and we do not offer them. There is no injection, pill or device that “permanently cures” erectile dysfunction while its cause continues. What produces lasting results is treating the cause and repairing the tissue, and then keeping the cause treated: for a man with prostatitis that means his prostate; for a man with diabetes, his sugar; for a smoker, stopping.
Treatment by stage of erectile dysfunction
Stage 1, mild: softer, less reliable erections
Treat the cause. In our clinic that usually means the prostatitis protocol, and most men at this stage recover full function from phase 1 alone, without any treatment to the penis. Lifestyle changes. A pill as a bridge if wanted. The tissue is intact; the aim is to keep it so.
Stage 2, moderate: the semi-rigid erection, lost during intercourse
Treat the cause, and begin GERP a few weeks in: the tissue has started to fibrose and the venous trap leaks. Six to eight weeks of the combined programme is typical. Most men regain reliable erections without a pill.
Stage 3, severe: rarely hard enough, pills failing
Treat the cause, and a full course of GERP, twelve to sixteen weeks, with PRP. Improvement is slower and builds over months; the goal is unassisted erections adequate for intercourse, and where that is not fully reached, erections with low-dose injections or a pill that now works again.
Stage 4, complete: no erection, including in sleep
Usually after surgery, radiotherapy or decades of disease. GERP preserves and partly rebuilds the tissue; intracavernosal injections give reliable erections for intercourse when the nerves cannot be restored; a penile implant is the last resort for the few in whom nothing else works, and we refer for it honestly when it is the right answer.
Erection pills: their place, and their trap
What they do
Sildenafil (Viagra), tadalafil (Cialis), vardenafil and avanafil boost the nitric oxide signal so that the penile arteries open more readily with stimulation. Taken one to three hours before sex, not more than once a day, they help most men with mild to moderate erectile dysfunction, and men with heart disease or on nitrates must have a doctor’s approval first. A daily low dose of tadalafil is also used as part of tissue rehabilitation, because keeping the chambers oxygenated slows fibrosis.
What they do not do, and the trap
They treat the symptom only. In a man whose erectile dysfunction comes from an inflamed prostate, the pill restores erections for a while, the cause is never looked for, the nerves and the tissue continue to be damaged, and within a year or two the pill works less well and the dose climbs. Repeatedly forcing erections in a congested, inflamed pelvis does the gland no favours either. Our rule: the day a man under 60 starts to need a pill is the day his prostate should be examined. The pill can then be kept as a bridge while the cause is treated, and most men no longer need it afterwards.
Erectile dysfunction after prostate surgery
Radical prostatectomy, and to a lesser degree surgery for benign enlargement, can bruise, stretch or cut the cavernous nerves that run along the prostate. When the nerves are cut, the damage is permanent and injections are the way to have erections. When they are bruised or stretched, which is the commoner case with nerve-sparing surgery, function returns gradually over twelve to twenty-four months, and the question is how much erectile tissue survives the wait: without erections the chambers are starved of oxygen and fibrose, so that when the nerves recover the tissue cannot respond.
This is what “penile rehabilitation” after surgery means, and GERP is built for it: early and regular oxygenation of the tissue with vacuum therapy and injections, shockwaves and PRP to support nerve regeneration and preserve smooth muscle, and daily low-dose tadalafil. Men who start within the first weeks after surgery recover more function, and sooner, than men who wait a year to “see what happens”. The same applies after radiotherapy and after pelvic surgery for bladder or bowel disease.
Stopping smoking, losing weight, exercising, eating less sugar and refined carbohydrate and more vegetables, drinking less, and keeping diabetes and blood pressure controlled all measurably improve erections and are part of GERP. On their own they rarely resolve established erectile dysfunction, because in most men the habit was an aggravating factor, not the origin. Together with treatment of the cause they make the result last.
Results, and what we tell every patient
What improves
The large majority of men who complete GERP, with the cause treated, report a significant and lasting improvement: firmer erections, erections that hold to the end of intercourse, the return of morning erections, better sensation, and in most men no further need for pills. Ejaculation and desire improve alongside, because they share the cause.
When the picture is mixed
In men with serious coexisting disease, diabetes, vascular disease, obesity, heavy smoking or drinking, a clear majority still improve, and the improvement lasts about two years or longer provided the man does his part: the habits change and the other conditions are kept under control. Without that, the gain fades.
When it will not work
If the cause is not treated. A man who wants GERP, shockwaves or PRP for the penis while declining to have his prostate treated will get little or temporary benefit, and we say so before we start. Treating the cause is not optional; it is the treatment.
Psychological factors, performance anxiety above all, are present in almost every man with erectile dysfunction. We do not treat them first, and we do not treat them alone, because in most men they are the reaction to a physical problem. They lift, usually without any specific help, as the erections return. What patients say afterwards.
Ready to treat the cause, not just the symptom?
Bring your history, your previous tests and the list of what you have tried. We examine the prostate, the vessels and the tissue in one visit and tell you which phase you need and how long it will take. Men come to Athens for this from across Europe and beyond.
Frequently asked questions about erectile dysfunction treatment
What is GERP?
The Georgiadis Erectile Revivification Protocol: a rehabilitation of the erectile tissue combining intracavernosal injections, vacuum therapy, low-intensity shockwaves and PRP in the same sessions, three times a week for six to sixteen weeks, begun once the cause of the erectile dysfunction, usually chronic prostatitis, is being treated.
Can erectile dysfunction from prostatitis be treated?
Yes, and it is the commonest form we treat. The prostatitis is treated first with the Georgiadis Protocol, which clears the inflammation and frees the strangled nerves of erection; early cases recover from that alone, and men whose erectile tissue has already fibrosed then receive GERP to repair it.
Does PRP work for erectile dysfunction, and how many injections are needed?
As part of a programme, yes: PRP is a regenerative stimulus that contributes to firmer erections and better sensation over weeks and months. On its own, in a penis whose nerves are still compressed by an inflamed prostate, it does little. We give three to six injections, four to six weeks apart, inside GERP. It does not enlarge a normal penis.
What does a P-shot look like before and after?
Ignore the photographs. The honest before and after is functional: an erection that comes more easily, holds longer and feels more, measured on penile Doppler as better arterial inflow and venous trapping. Many men also notice a fuller-looking penis as the tissue recovers. Results build gradually and depend on the cause being treated.
Is there a permanent cure for erectile dysfunction?
No product cures it permanently while its cause continues. What lasts is treating the cause, repairing the tissue, and keeping the cause under control. Most men who complete both phases with the cause treated keep their result.
Do stem cell injections work for erectile dysfunction?
They are experimental: small studies, unregulated products, no proven advantage over PRP and shockwaves. We do not offer them.
Which treatment is right for my stage of erectile dysfunction?
Mild: treat the cause, usually enough on its own. Moderate: treat the cause and a six-to-eight-week course of GERP. Severe: the cause plus a full twelve-to-sixteen-week course with PRP. Complete: tissue preservation with GERP, injections for intercourse, and an implant only as a last resort.
How do I speed up nerve recovery after prostate surgery?
Start rehabilitation early: vacuum therapy and low-dose injections to keep the tissue oxygenated, shockwaves and PRP to support nerve regeneration and preserve smooth muscle, and daily low-dose tadalafil. Men who begin in the first weeks recover more function than men who wait to see what happens.
Should I keep taking Viagra or Cialis during treatment?
If they are safe for you, yes, as a bridge, and a daily low dose of tadalafil is part of tissue rehabilitation. Most men no longer need them once the cause is treated and the tissue has recovered.
